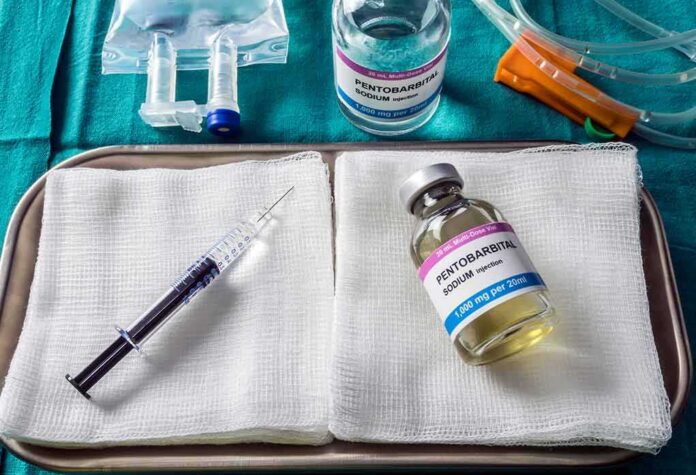
Tennessee’s halted attempt to execute Christa Gail Pike after two doses of lethal drugs shows how often lethal injection can still fail to work as promised.
Story Snapshot
- Tennessee’s recent failed lethal injection highlights system errors that can prolong suffering.
- Researchers and trackers say lethal injection is the most frequently botched execution method.
- At least eight lethal-injection executions since 2019 have been bungled, according to one analysis.
- The Supreme Court has said evidence of past faulty executions matters in method challenges.
What “failure” means in lethal injection debates
Policy groups and scholars define a botched execution as one with unplanned problems or delays that may cause needless pain or show serious errors by staff. Death penalty researchers say lethal injection has more such problems than any other method. An analysis from the Death Penalty Information Center states it is the most often botched method in modern use, which shapes lawsuits and public opinion about its humaneness.
Courts also weigh this record. In a 2023 order, the United States Supreme Court recognized that proof of past faulty or failed executions is relevant in challenges to a state’s chosen method. That stance signals that governments must show their procedures reduce known risks, not simply claim they work. Litigation now often turns on drug choice, dose, staff training, and how states monitor pain and airway during the process.
The Tennessee case that reignited scrutiny
Tennessee officials attempted to execute Christa Gail Pike by lethal injection, but the process did not reach its planned end. Reports and court filings say staff administered two doses of a lethal drug before the execution was halted. Her lawyers then sought orders to preserve evidence, saying she remained unconscious, intubated, and on a ventilator in a hospital after the attempt. Questions center on whether intravenous lines were properly placed.
Attorneys argued that a misplacement of the lines may have sent the drug into tissue rather than into a vein, which would undercut the intended effect and extend distress. They also pressed for chain-of-custody protection for syringes, lines, and equipment to enable an independent review. The state’s halted execution underscores how line access and drug delivery remain failure points, even with a single-drug protocol meant to simplify the process.
How often lethal injection goes wrong, and why that matters
Since 2019, at least eight lethal-injection executions have been bungled, according to a review cited by Northeastern University’s news service. The same reporting points to a wider pattern in which intravenous access problems, drug sourcing issues, and monitoring gaps lead to delays, visible distress, or procedure stoppages. These events feed a cycle: each failure triggers new policies, yet the core risks of line placement and drug effects persist.
The Death Penalty Information Center’s review states lethal injection “goes wrong” more than other methods, a claim tied to recurring errors that are hard to detect in real time. Medical literature and news explain why: finding veins can be hard, especially for people with poor vascular access, and high-dose sedatives may still allow lung fluid buildup, which causes air hunger. When teams cannot set a reliable line, the execution can drag or fail.
Shared concerns across the political divide
Families on both sides of a capital case expect the state to act with control and transparency. When an execution stalls after drug delivery, trust drops further. Many Americans, right and left, see a government that cannot deliver basic competence yet demands broad power over life and death. Whether one opposes or supports capital punishment, a process that misfires feeds the view that elites manage risk for themselves, while regular people face the harm and the bills.
The AMA ethics state “a physician must not participate in a legally authorized execution.” The ban is total, including giving technical advice. Physicians may only certify death after someone else has already declared it. Most states require a physician be present. 1/4
— Debra Fulton (@juniebegood2me) October 4, 2026
The Supreme Court’s position means each failure carries legal weight. States that press ahead without reforms face more court scrutiny and more delays. Documented errors, like failed intravenous access, now become evidence, not footnotes. That legal shift raises a simple test most citizens would accept: if the government insists on using the ultimate penalty, it must first prove the method works as claimed, every time, under clear rules the public can check.
Sources:
youtube.com, supremecourt.gov, agingwithdignity.org, compassionandchoices.org
© primechronicle.org 2026. All rights reserved.